PGT-An
Preimplantation Genetic Testing (PGT-A)
Chromosome analysis of embryos using next-generation sequencing — to transfer the embryo most likely to succeed.

PGT-An
Chromosome analysis of embryos using next-generation sequencing — to transfer the embryo most likely to succeed.
Technology
Biopsy
Reduces miscarriage risk
Decision-making
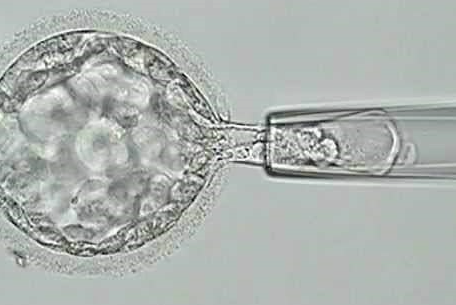
PGT-A (Preimplantation Genetic Testing for Aneuploidies) analyzes the chromosome composition of embryos through a small biopsy performed on day 5–6, at the blastocyst stage. The goal is to identify chromosomally normal (euploid) embryos before transfer, reducing the probability of failed implantation and pregnancy loss.
A chromosomally abnormal embryo either fails to implant or results in an early miscarriage. By selecting euploid embryos for transfer, PGT-A aims to improve the outcome of each individual transfer attempt.
Early preimplantation genetic screening (formerly called PGS) used FISH technology, which had significant limitations — it could only analyze a subset of chromosomes and had meaningful error rates. Modern PGT-A uses Next-Generation Sequencing (NGS), which provides comprehensive chromosome analysis of all 23 pairs with much higher accuracy.
The shift from day-3 to day-5/6 biopsies has also substantially improved both accuracy and embryo viability after the biopsy procedure. Day-5 trophectoderm biopsy samples cells from the outer layer of the blastocyst — cells that will become the placenta, not the embryo itself.
PGT-A is supported by evidence for: higher live birth rates per embryo transfer; shorter time to pregnancy (fewer transfer attempts before success); and reduced miscarriage rates in selected patient populations.
However — and this is important — there is no evidence that PGT-A improves cumulative live birth rates (total babies born across all attempts using all embryos from a retrieval cycle). In some cases, it may actually decrease them by removing embryos that carry chromosomal mosaicism — a condition where some cells are normal — but could have implanted successfully. The decision to use PGT-A should weigh these tradeoffs carefully, and Dr. Glujovsky discusses them transparently with each patient.
PGT-A is most valuable for patients who want to reduce the number of transfers before achieving pregnancy, patients with recurrent miscarriage (two or more pregnancy losses), patients with a previous aneuploid pregnancy, and patients over 38 — where the rate of chromosomally abnormal embryos rises substantially.
It is less clearly beneficial for younger patients with good ovarian reserve and many untested embryos available. In those cases, the cumulative live birth rate is already high without testing, and PGT-A adds cost and procedural complexity without a clear net benefit.
That said, many younger patients choose to include PGT-A anyway — not because it changes their overall odds, but because they prefer to reduce the number of transfers on the path to a baby, or because they want more information about the embryo before transferring it. Both are valid reasons, and the decision should always be individualized, not protocol-driven.

In vitro fertilization with personalized protocols and blastocyst-stage transfer (with or without PGT-A.

60–70% pregnancy rate per transfer. Minimum 8 mature eggs guaranteed (or 10 if you choose to include PGT-A). Blastocyst transfer.

Preserve your fertility with vitrification while your eggs are at their best.
Contact
Dr. Glujovsky will review your history, explain your options honestly, and tell you exactly what he believes is the right path for you — not a generic protocol. Initial consultations can be in person or via video call from anywhere in the world.